

The Mindbloom Method is clinically validated across the 3 largest peer-reviewed studies of ketamine therapy ever published.
All three showed stellar outcomes across anxiety, depression, PTSD, and more.






Mindbloom’s research archive





At-home, telehealth-supported ketamine therapy for veterans with depression, anxiety, and PTSD: Findings from a real-world, observational study



Mindbloom is committed to advancing psychedelic science, with the largest body of research of any ketamine therapy provider following more than 11,000 clients.
Symptom improvement
reported symptom improvement in anxiety & depression1
reported meaningful PTSD symptom improvement2
with suicidal thoughts reported them fully resolved within program completion1

Speed to results
Not only does our at-home ketamine program greatly reduce feelings of anxiety and depression, it does so in hours or days—not months.
Mindbloom1
Hours to days
Tradtional SSRIs3
4-8 weeks

With traditional treatments, people might not notice improvements for up to 2 months—that is, if they see improvements at all. Because of ketamine’s fast-acting nature, most Mindbloom clients report symptom relief after just 4 sessions, and some after their very first session.

Side effects
experienced no side effects with Mindbloom treatment1

Many come to Mindbloom frustrated by side effects of their SSRIs (weight gain, emotional flatness, loss of libido). Our peer-reviewed studies demonstrate the high tolerability profile of this treatment. The mild effects that may occur typically clear within hours. That's why people finish their programs, and why Mindbloom’s care model actually works.

Treatment comparisons
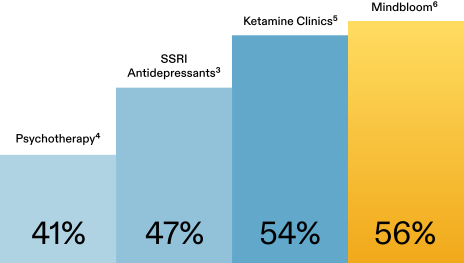
When compared to studies of alternative treatments, Mindbloom’s symptom improvements were stronger and achieved in just 4 weeks vs 2+ months.

Sleep
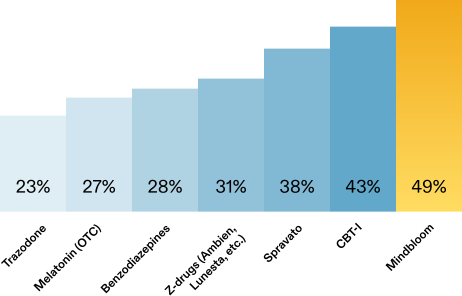
The largest ketamine sleep analysis to date saw clients report significant improvement—better than Ambien, trazodone, melatonin, and CBT for insomnia—often visible after just 2 Mindbloom sessions.7
saw clinically meaningful improvement in sleep

Veterans
The largest evaluation of ketamine therapy in veterans ever published saw tremendous outcomes across anxiety, depression, and PTSD.8
Ketamine has been used safely and effectively for mental health for 20+ years.
With over 300 major studies conducted across 50+ institutions, clinical research continues to demonstrate that ketamine can be successfully used to treat mental health conditions and their symptoms.
Ketamine for Depression, 4: In What Dose, at What Rate, by What Route, for How Long, and at What Frequency?
Ketamine, administered in subanesthetic doses, is an effective off-label treatment for severe and even treatment-refractory depression; however, despite dozens of studies across nearly 2 decades of research, there is no definitive guidance on matters related to core practice issues.
A Double-Blind, Randomized, Placebo-Controlled, Dose-Frequency Study of Intravenous Ketamine in Patients With Treatment-Resistant Depression
Double-blind study evaluating the efficacy of intravenous ketamine administration in sustaining antidepressant effects in treatment-resistant depression patients, finding significant improvements in depression scores.
Acute Antidepressant Effects of Intramuscular Versus Intravenous Ketamine
IM ketamine in the dose of 0.25 mg/kg is as effective and safe as 0.5 mg/kg given either I.M. or I.V., substantially alleviating depressive symptoms within a few hours and sustained for 3 days.
Antidepressant, mood stabilizing and procognitive effects of very low dose sublingual ketamine in refractory unipolar and bipolar depression
Our clinical observations were that VLDS ketamine produced rapid and robust effects on mood, sleep and cognition in around 75% of patients, with very good tolerability in most cases. The effect on sleep was often reported as remarkable for inducing a deep and repairing sleep, in line with previous findings of increased slow wave sleep by ketamine injection (Duncan et al., 2012). Also, some patients retained their therapeutic response even after stopping ketamine treatment, which may be associated with the strong neuroplastic changes produced by ketamine, as shown in animal studies (Duman and Aghajanian, 2012), but longer and more systematic observations are necessary.
You deserve proof, not promises.

Hull TD, et al. Journal of Affective Disorders (2022). https://doi.org/10.1016/j.jad.2022.07.004.
Parks AC, et al. Journal of Medical Internet Research (2026). https://doi.org/10.2196/92647.
Trivedi M,. et al. American Journal of Psychiatry (2006). https://doi.org/10.1176/appi.ajp.163.1.28.
Cuijpers P, et al. Acta Psychiatrica Scandinavica (2021). https://doi.org/10.1111/acps.13335.
McInnes L. A., et al. Journal of Affective Disorders (2022). https://doi.org/10.1016/j.jad.2021.12.097.
Mathai DS, et al. Journal of Affective Disorders (2024). https://doi.org/10.1016/j.jad.2024.05.131
Swain et al., Research Square (2026). https://doi.org/10.21203/rs.3.rs-9553669/v1.
Lutz et al., Manuscript in preparation (2026)

